Ask ten people how much life insurance they have and most of them will give you a round number — $250,000, $500,000, whatever sounded big enough when they signed up. Ask them how they picked that number and you mostly get a shrug.
That shrug is the problem. Life insurance isn’t supposed to be a round number. It’s supposed to cover what your family would still owe, still need, and still want to pay for if you weren’t there. When the number comes from a guess, it usually comes up short.
The industry’s own research backs that up. In the 2025 LIMRA and Life Happens Insurance Barometer Study, only 51% of American adults said they had any life insurance at all, and close to 100 million adults said they need coverage or need more than they have. Nearly half said their loved ones would barely be financially secure — or not secure at all — within six months if the main earner died. That’s not a sales statistic. That’s a lot of families one paycheck away from trouble.
So let’s do the math properly. It takes about ten minutes, and you only need four buckets.
Start with what you owe
Write down every debt that wouldn’t disappear if you died: credit cards, car loans, student loans, medical bills, any personal loans. Then add final expenses. Funerals aren’t cheap, and your family shouldn’t have to put that on a credit card while they’re grieving.
This bucket is the most straightforward one. It’s money your family would owe on day one, so it goes in first.
Replace the income
This is the bucket most people underestimate. If your family depends on your paycheck to pay the rent, buy groceries, and keep the lights on, ask how many years of that income they’d need to get back on their feet.
A common starting point is 10 times your annual income. It’s a rule of thumb, not a verdict — a family with young kids and one income needs more years of replacement than a two-income couple with no kids and a paid-off house. Think about how long it would take your spouse to adjust, retrain, or rebuild, and be honest about it. Five years sounds generous until you picture a single parent doing it alone.
Cover the house
If you have a mortgage, your family faces a hard choice after a death: keep paying it on one income, sell the house in a hurry, or lose it. Plenty of families put the full remaining mortgage balance in their coverage number so that choice never has to happen. If your plan is for your spouse to keep the house, this bucket matters more than almost any other.
Renters, don’t skip this one either. Your family still needs a place to live, and a year or two of rent in the number buys them time to decide without panic.
Set aside education money
If you have kids and you want them to have a shot at college, price it in. You don’t need to fund four years at a private university — just decide what you’d want to leave toward it and write that number down. The same goes for any other promise you want to keep: helping a parent, leaving something to a charity, covering a child’s wedding someday. Life insurance is one of the few tools that lets you keep a promise after you’re gone.
Now subtract what you already have
Add the four buckets up. Then subtract what your family would already get: savings and investments they could use, any life insurance you already own, and Social Security survivor benefits if your family qualifies. The National Association of Insurance Commissioners’ buyer’s guide makes exactly this point — count what you already have before you decide what you still need.
And check your work coverage with clear eyes. A lot of people tell me they have life insurance through their job, and they do — usually one or two times their salary, and usually only while they work there. Change jobs, get laid off, retire, and it’s gone. Work coverage is a nice bonus. It’s a shaky foundation for a family’s whole plan.
What you’re left with after the subtraction is your real number. For a lot of young families, it’s bigger than the round number they guessed — often $750,000 to $1 million or more. That surprises people. Then they see the price and it surprises them again, in the good direction.
What it actually costs
Here’s the part that stops most people from ever running the numbers: they assume life insurance costs far more than it does. LIMRA’s research keeps finding the same thing — a large share of Americans overestimate the cost, many of them wildly, often because they’re guessing off a feeling rather than a quote.
For a healthy non-smoker, $500,000 of 20-year term coverage often lands somewhere around $20 to $40 a month at age 30, $35 to $60 at 40, and $100 to $140 at 50. Those are benchmarks, not quotes — your rate depends on your age, health, and the carrier — but the pattern holds: younger and healthier means cheaper, and waiting costs you twice, once in age and once in health. A health scare in your 40s can change your rate more than a decade of birthdays.
Term coverage costs a fraction of permanent coverage for the same death benefit, because it covers a set number of years and builds no cash value. For most families, that’s the right tool for this job: cover the years when the mortgage is big, the kids are young, and the income matters most. If you want lifelong coverage or a cash-value piece, that’s a different conversation, and it starts with the same number.
The only wrong answer is a guess
You don’t need to get this number perfect to the dollar. You need it to come from your debts, your income, your house, and your kids — not from a round number that sounded fine at a benefits fair five years ago.
Sit down with the four buckets this week. Add them up, subtract what you have, and look at the gap. If the gap is zero, great — you’re covered, and you can stop worrying about it. If it isn’t, a ten-minute phone call can close it, usually for less per month than most people spend on streaming services they forgot they had.
Your family shouldn’t have to guess how to get by. Give them a number that actually holds up.
Questions about your number? I’m here for them. Call me at (623) 742-3878 or visit www.azhealth.us — I answer my own phone, and I’ll run the numbers with you for free.
You just combined your lives. Bank accounts, a lease or a mortgage, maybe a shared car payment and a pile of wedding gifts that still need thank-you notes. One conversation most newlyweds skip: what happens to all of that if one of you dies?
It’s not a fun question. It’s also the cheapest question you’ll ever answer — because life insurance for newlyweds is priced on two things, your age and your health, and right now both are working in your favor.
Why life insurance for newlyweds is cheapest right now
A healthy nonsmoker in their late 20s can often get a $500,000, 20-year term policy for somewhere around $22 to $35 a month. Wait until 45 and that same policy can cost two or three times more. Wait until a health problem shows up — a diagnosis, a new prescription, a surgery — and the price jumps again, or the answer becomes no.
That’s the part people miss: you don’t buy life insurance with money. You buy it with your health, and you pay for it with money. The day you’re young and insurable is the day it’s cheapest. Every birthday after that, the same coverage costs more.
Term life: the most coverage for the least money
Term life is pure protection for a set number of years — 10, 20, or 30. If you die during the term, your spouse gets the check. If you outlive it, the policy ends.
Why young couples like it:
Biggest death benefit per dollar, by far
It covers exactly the years when the need is biggest: the mortgage balance, the years kids are at home, the years your income matters most
Most policies are convertible, meaning you can swap some or all of it to a permanent policy later without a new medical exam, as long as you do it before the conversion deadline
The downside is simple: when the term ends, so does the coverage. Starting over at 55 is expensive.
Whole life: the part that’s yours forever
Whole life never expires. The premium never goes up, and the policy builds cash value you can borrow against down the road. If it’s a participating policy from a mutual company, it may also pay dividends — not guaranteed, but many carriers have paid them for decades.
Why it matters for a young couple:
It’s guaranteed to pay out someday, which makes it the right tool for final expenses and anything you want covered for life
You lock your insurability in permanently. Health changes later can’t touch it
The cash value grows tax-deferred
The trade-off: the same amount of coverage costs much more than term. On a newlywed budget, whole life alone usually can’t buy enough coverage to replace an income.
Universal life: permanent coverage with flexibility
Universal life is permanent like whole life, but flexible. You can raise or lower your premium within limits, adjust the death benefit, and the cash value grows based on interest the carrier credits. Indexed universal life ties that growth to a market index with a floor, so it can’t go below zero in a down year.
Why some couples pick it:
Premiums can flex when life does — a new baby, a job change, one spouse going part-time
More growth potential than a traditional whole life policy
The honest catch: it’s not a set-it-and-forget-it policy. If you underfund it for years, the rising internal cost of insurance can eat the cash value when you’re older. It needs an annual review. Handled right, it’s a strong middle option between term and whole life.
The move most young couples actually make: combine them
You don’t have to pick one. The setup I recommend most often for couples in their 20s and 30s looks like this:
A smaller whole life policy ($25,000 to $50,000) as a permanent base — final expenses and coverage that’s there for life
A larger term policy ($500,000 or more) on top, sized to the mortgage and the income-replacement years
For a healthy couple in their late 20s, that combination often lands around $65 to $90 a month per person. Examples only — your rate depends on the carrier, your health, and underwriting.
There’s also laddering: two term policies instead of one. A 30-year term to cover the mortgage and a 20-year term to cover the years until the kids are grown. When the 20-year policy drops off, the premium drops too — because the need did.
And as your income grows, you can convert part of the term into permanent coverage before its conversion deadline runs out. Your 40-year-old self will thank you.
How much do you need?
Quick math: 10 to 15 times your income, plus the mortgage and other debts, minus whatever savings you have. The shorthand is DIME: Debts, Income, Mortgage, Education. For most young couples, that lands between $500,000 and $1,000,000 each.
Each. Both spouses need a policy — including a spouse who stays home. Childcare and running a household would cost real money to replace.
One more thing: the life insurance at your job is usually only one or two times your salary, and it stays behind when you change jobs. It’s a supplement, not a plan. You can read more about your options on my life insurance page.
Want a neutral primer first? The National Association of Insurance Commissioners has a consumer guide to life insurance that walks through the basics.
The bottom line
You’ll never be younger than you are today, and you probably won’t be healthier. Get the quote while both are true. It costs nothing to look, and the rate you lock in now follows you for the entire policy.
I’m Andy Orlikoff, an independent broker in Surprise. I shop multiple carriers, you pay the same rate as going direct, and I answer my own phone.
Questions? Call or text me at (623) 742-3878 or visit www.azhealth.us.
2027 ACA open enrollment Arizona starts November 1 — and if you buy your own coverage, this is not a year to let your plan renew on autopilot.
Blue Cross Blue Shield of Arizona is replacing, renaming, or redesigning every single one of its ACA plans for 2027. Premiums are jumping about 25% on average. And your renewal letter — already in the mail — moves you to a brand-new plan whether you read it or not. Here’s what’s changing and what to do about it.
First, the dates for 2027 ACA open enrollment Arizona
On HealthCare.gov — which is what Arizona uses — open enrollment runs November 1, 2026 through January 15, 2027.
Enroll by December 15 and your coverage starts January 1.
Enroll December 16 through January 15 and it starts February 1.
Miss the window and you’re locked out until 2028, unless you qualify for a special enrollment.
Your BCBSAZ plan isn’t renewing — it’s being replaced
This is the big one. Blue Cross Blue Shield of Arizona says all of its current ACA plans are being replaced, renamed, or redesigned for 2027, and every renewing member gets mapped to a new plan.
“Auto-mapped” sounds harmless. It isn’t. A new plan can mean a new network, a new deductible, new copays — and a new price. BCBSAZ mailed renewal notices by October 16 with a personalized plan comparison showing exactly where you’re landing. If that letter is sitting unopened on your counter, open it. It’s the single most important piece of mail you’ll get this month.
One more thing: no BCBSAZ plan will require a primary care provider assignment in 2027. The trade-off — their PCP Guided Care plans do require specialist referrals, to keep your care coordinated.
And if you had Cigna, you’re shopping no matter what: Cigna is leaving Arizona’s individual market on January 1, so about 2,500 Arizonans need new coverage.
Premiums are going up — about 25% on average
BCBSAZ told brokers to expect individual and family premiums to rise by an average of about 25% for 2027 ACA open enrollment Arizona. How much your premium actually moves depends on your age, your county, the plan you pick, and — maybe most of all — your subsidy.
That’s the part people underestimate. Your tax credit is recalculated every year from the income and household info in your HealthCare.gov account. BCBSAZ specifically urges clients to update their information, because subsidy eligibility can swing your monthly premium dramatically.
Here’s the wrinkle nobody’s talking about enough: the extra federal subsidies from the pandemic years are gone — Congress let them expire at the end of 2025. For 2027, premium tax credits follow the old rules: households between 100% and 400% of the federal poverty level can qualify, and above that cliff the credit drops to zero. A raise or a strong year of self-employment income can push you over that line. Get your income estimate right. ACA subsidies in Arizona: how they work →
For context on how rough this year is: Arizona’s proposed average increase across all carriers is around 29% — the highest of any state in the country. The full breakdown is here →
What’s new and better for 2027
It isn’t all bad news for 2027 ACA open enrollment Arizona — a few real improvements are coming:
Prosano Health grows up. Four plan options across Bronze, Silver, and Gold in Maricopa and Pima counties. Prosano members get primary, preventive, and sick care at Prosano Health Care Centers included at no additional cost — and BCBSAZ reports a 92% net promoter score from members.
The ACA Health Choice network is expanding to 12 Arizona counties, aimed at simplifying networks in rural counties while keeping provider access broad.
Plan designs are getting friendlier. BCBSAZ promises more predictable out-of-pocket costs, lower deductibles on select plans, and fixed copays for many common services — so you know what a doctor visit costs before the bill shows up.
One heads-up: the federal ceiling on what a marketplace plan can make you pay for covered in-network care rises to $12,000 for an individual and $24,000 for a family in 2027. Comparing deductibles and copays matters as much as the premium.
Healthcare.gov isn’t your only option
Here’s what the marketplace mailers won’t tell you: I also have plans outside of healthcare.gov — and for the right person, they can cost less than what’s on the exchange.
These aren’t for everyone. But if you’re healthy, self-employed, between jobs, or just priced out of the marketplace, an off-marketplace plan can be a real alternative. Affordable PPO alternatives in Arizona → Don’t assume your only choice is a pricier ACA plan until you’ve seen both sides.
Three things to do before December 15 for 2027 ACA open enrollment Arizona
Open your renewal letter. Read the personalized plan comparison. Know exactly which plan you’re being mapped to and what it costs.
Update your HealthCare.gov info. Income, household size, address — all of it. Your 2027 subsidy is only as accurate as what you enter.
Talk to someone who answers the phone. Don’t let an algorithm pick your 2027 plan. A ten-minute conversation can save you from a year of the wrong coverage. Reach me here →
For 2027 ACA open enrollment Arizona is a rebuild year for ACA plans. The carriers are reshuffling everything, prices are up, and auto-renewal is a gamble this time. Take twenty minutes, read your letter, and make an actual decision. You’ll thank yourself in January.
Medicare Advantage plans get marketed hard every fall. Zero-dollar premiums, dental, vision, gym memberships — the commercials make it sound like a no-brainer. And for some people, it works out fine.
But going into 2027, the ground is shifting. CMS finalized its 2027 payment rates for these plans: a 2.48% net increase, which works out to about 5% once expected risk-score trends are included. Insurers say even that isn’t keeping pace with what care actually costs — Humana has already told investors it plans to adjust benefits where necessary next year. When money gets tight, benefits are usually where it shows. (For balance: CMS says about 8 in 10 MA enrollees can keep their current plan at the same or a lower premium in 2027, with average premiums ticking down slightly.)
I don’t sell Medicare Advantage, and I’ve put my reasons in writing. But whether you work with me or not, here are six Medicare Advantage disadvantages worth knowing before the year turns.
1. Prior authorization can delay the care you need
Original Medicare has historically made you ask permission far less often than Advantage plans do. A 2026 report from the HHS Office of Inspector General looked at skilled nursing facility admission requests from June 2024, across 19 parent companies covering about 86% of MA enrollment. Plans denied 12% of those requests — and when patients or providers appealed, the plans overturned 95% of the denials. The OIG’s read: some enrollees were initially denied care that was medically necessary. One detail that sharpens the point: only about 18% of those denials were ever appealed. Appeals take time, and if you’re recovering from surgery or a hospital stay, time matters.
One caveat, especially here in Arizona: starting in 2026, CMS began testing prior authorization inside Original Medicare itself, under a pilot called WISeR. It covers six states including ours, and a defined set of outpatient services — narrower than what Advantage plans do, but the line isn’t as clean as it used to be. A Medigap policy doesn’t change that part.
2. Networks decide where you can go
Original Medicare lets you see just about any doctor or hospital in the country that takes Medicare. (For perspective: KFF found Advantage plans included just under half — 48% — of the physicians available to traditional Medicare beneficiaries.) Medicare Advantage HMOs generally require you to stay in-network except for emergencies; PPOs give you some out-of-network coverage, but you’ll pay more for it.
That’s manageable until your longtime specialist leaves the network — and network limits are among the most common Medicare Advantage disadvantages I hear about — or the hospital you trust isn’t covered anymore. It hits harder outside the cities: in 2026, KFF found beneficiaries in the most rural counties had about 20 plans to choose from on average, versus 42 in urban areas — and KFF’s 2027 data shows options shrinking again, with the average beneficiary seeing 28 drug-included plans, down from 32.
3. The low premium and extra perks can shrink
That $0 premium and the dental, vision, and over-the-counter allowances reset every year. Plans can raise premiums, increase copays, and trim supplemental benefits each January. Going into 2027, with insurers openly planning benefit adjustments, the plan that worked great this year can look very different next January — more expensive, less generous, or both.
4. Your drug coverage can change under you
Most Medicare Advantage plans bundle in Part D drug coverage, and formularies, pharmacy networks, and coverage rules can all change annually. A medication can move to a higher cost tier or pick up new restrictions in the new plan year. Checking that your premium didn’t change isn’t enough — run every regular prescription through Medicare’s Plan Finder tool before you renew.
5. Your plan can disappear entirely
Sometimes the change is bigger than a benefit tweak: an insurer can drop a specific plan or leave your county altogether. When a plan’s contract actually ends and you don’t pick another Advantage plan, you’re generally moved to Original Medicare — and that move comes with a 63-day window where you have a federal guaranteed right to buy certain Medigap policies. That protection doesn’t apply if your plan was merely consolidated into another one of the insurer’s plans, so it matters which kind of change you’re dealing with.
Either way, it can be genuinely disruptive if you’re in the middle of cancer treatment, rehab, or another complex course of care. New plan, new doctors, new pharmacies, new copays.
6. Getting back to Original Medicare can be harder than leaving was
This is the one people miss. You can leave Medicare Advantage and return to Original Medicare during an enrollment period — but that doesn’t automatically mean you can buy a Medigap policy to cover Original Medicare’s deductibles and coinsurance. Outside your six-month Medigap open enrollment window or a guaranteed-issue situation, insurers in most states can charge you more or deny you based on your health.
Two exceptions worth knowing. First, the trial right: if you joined Medicare Advantage when you first became eligible and leave within the first year, federal law gives you guaranteed-issue rights to buy a Medigap policy. Second, as noted above, if your Advantage plan’s contract ends or it stops serving your area, you generally get that 63-day guaranteed-issue window. But if you leave voluntarily while your plan keeps operating — and you’re past your trial year — you may not have that protection. (A few states are more protective than the federal baseline, so this is a check-your-state situation.)
What to do about these Medicare Advantage disadvantages
I’m not telling you Medicare Advantage is never the right call. I’m telling you to go in with your eyes open — especially for 2027, with plan data already live and open enrollment underway.
Your Annual Notice of Change should have arrived by September 30. If you haven’t seen yours, call your plan. It spells out exactly what’s changing in January. Then check the things that actually matter to you: your doctors, your hospitals, your prescriptions, your premium, your maximum out-of-pocket, and those supplemental benefits. Don’t assume this year’s coverage carries forward unchanged.
And if you’d rather have coverage built for stability — standardized Medigap benefits that are guaranteed renewable, no networks, no disappearing plans — that’s exactly what I do — I help people compare these Medicare Advantage disadvantages against what a supplement offers. Two honest caveats: the standalone Part D drug plan you’d pair with Medigap does change yearly (options are shrinking for 2027, and some buyers face steep premium jumps), and Medigap premiums themselves can rise over time. But the core medical coverage doesn’t reset every January. I’ve explained my thinking here: why I don’t sell Medicare Advantage.
Medicare open enrollment runs October 15 through December 7. If you want a straight answer about what your options actually look like, call or text me at (623) 742-3878. I’ll run your numbers free.
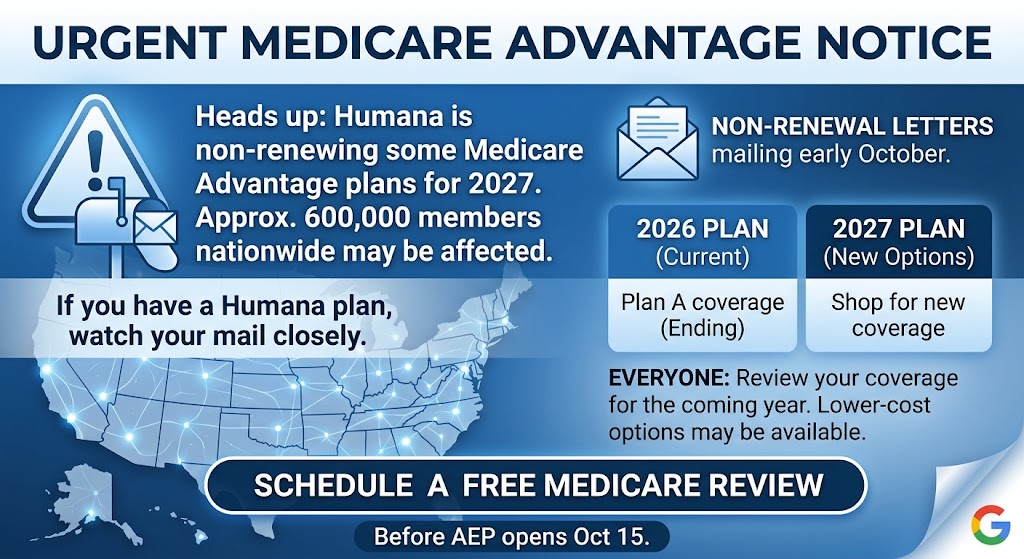
Humana has confirmed it’s exiting a number of Medicare Advantage plans for 2027, affecting roughly 600,000 members nationwide. If you have a Humana Medicare Advantage Arizona plan, this is worth paying attention to — whether or not you’ve received anything in the mail yet.
What’s actually happening
Humana is discontinuing plans it says are the “lower tail of profitability” for 2027 — mostly plans rated 3.5 stars or lower. Non-renewal letters are expected to go out starting in early October, right as Medicare’s Annual Enrollment Period opens on October 15. If your plan is affected, you’ll be notified directly by Humana, but the letter alone won’t tell you what to do next.
Why this matters even if you’re not sure you’re affected
Humana hasn’t published a full list of which specific plans or counties are impacted. The only way to know for certain is to watch your mail closely this fall — and to have a plan for what comes next if a non-renewal letter shows up. Waiting until you’re holding the letter to start comparing options means doing it under time pressure, right in the middle of AEP’s busiest weeks.
Humana Medicare Advantage Arizona: Your Options If Your Plan Is Dropped
If your Humana Medicare Advantage plan is discontinued, you’re not left without coverage — you’ll have a special enrollment window to pick something new. Depending on your situation, that could mean:
Enrolling in a different Medicare Advantage plan from another carrier
Moving to Original Medicare paired with a Medicare Supplement (Medigap) plan and a stand-alone Part D drug plan
Reviewing whether your current doctors and prescriptions are still covered under any new option you’re considering
As an independent Arizona broker, I’m not tied to steering you back into another Humana Medicare Advantage Arizona product — the goal is finding whatever actually fits your coverage needs now.
What to do this fall
Whether or not you get a letter, it’s worth a quick check-in before AEP opens October 15. If you are notified that your plan is being discontinued, reach out as soon as you get the letter — the sooner we start comparing options, the less rushed the decision.
Received a non-renewal letter, or just want to make sure you’re covered either way? Call (623) 742-3878 for a free, no-pressure review. As an independent Arizona health insurance broker, I can also show you how a Medicare Supplement plan works if you would rather not depend on one plan’s network and market decisions.
This article is for general educational purposes and is not a comparison of specific plans or an endorsement by Medicare, Humana, or any government agency. Please review any notice you receive directly from your carrier for details specific to your plan.
Andy Orlikoff • NPN #7558435 • Licensed in Arizona, North Carolina & South Carolina
Verify this license at nipr.com Follow us on Facebook