
Medicare Parts A and B Aren’t Full Coverage: The Uncapped 20% Most People Miss

If you ask most people turning 65 what Medicare covers, they’ll tell you it covers everything. They’ve paid into it their whole working life, so it stands to reason — right?

Not quite. And this is the conversation I have more than any other during Medicare open enrollment: Original Medicare — Parts A and B — is good coverage, but it is not full coverage. There’s a gap in it, and the gap has no ceiling.

Here’s the part that surprises people: under Original Medicare, there is no yearly limit on what you pay out of pocket. Medicare.gov says it plainly — there’s no annual out-of-pocket maximum unless you have supplemental coverage. Part B pays 80% of the Medicare-approved amount for your care. You pay the other 20%. And that 20% never stops.

Medicare Parts A and B 20 percent

The 20% that never caps out

Most health insurance you’ve had through a job came with an out-of-pocket maximum — a number where the plan takes over and pays 100%. Original Medicare doesn’t have one. The 20% coinsurance on Part B applies to doctor visits, outpatient care, outpatient surgery, X-rays and scans, equipment like walkers and wheelchairs, and the doctor services you get while you’re in the hospital.

Here’s where it adds up. The 20% isn’t a one-time hit on one big bill — it’s a slice of almost every doctor visit, every scan, every therapy session, every outpatient procedure, all year long. Regular treatments for a serious condition can run into the tens of thousands of dollars in Medicare-approved costs in a single year, which means thousands of dollars out of your pocket in 20% shares — and there’s no point in the year where it stops. Next year, it starts over. One rough year can turn into two, and the 20% just keeps coming.

Medicare covers a lot, but it was never built to cover everything. And nobody mails you the missing piece — you have to know to ask for it.

Part A has its own bills, too

Part B isn’t the only place the costs add up. Part A, the hospital part, has a $1,736 deductible in 2026. It isn’t once a year. Medicare counts it per “benefit period” — basically, a hospital stay plus 60 days out of care before the clock resets. Two separate stays in one year can mean paying it twice.

Long stays get expensive on their own. After the deductible, days 61 through 90 in the hospital cost $434 a day in 2026. Days 91 through 150 cost $868 a day — Medicare calls these your “lifetime reserve days,” a one-time bank of extra days that doesn’t refill once you’ve used them. After day 150, you pay all costs. Skilled nursing facility care after a qualifying hospital stay runs $217 a day for days 21 through 100.

And your Part B deductible — $283 for the year in 2026 — comes out of your pocket before Medicare starts paying its 80%.

Those aren’t small numbers. Stack a few of them in a rough year and it can take a real bite out of your savings. And a note on the figures: these are the 2026 amounts — CMS usually announces the next year’s numbers in mid-November.

The fix: a Medicare Supplement fills the gap

This is where a Medicare Supplement — a Medigap plan — comes in. It sits on top of Original Medicare and pays the costs Medicare leaves behind. My standard recommendation for most people is Plan G, and the company I usually start with is Physicians Mutual.

Here’s what Plan G covers, straight from Medicare.gov’s plan comparison — and if you want the deeper dive, my Medicare Plan G page for Arizona walks through it in detail:

  • Your Part A deductible — 100%
  • Your Part B coinsurance and copayments — 100%
  • Part B excess charges (the extra a doctor is allowed to bill on top of Medicare’s price) — 100%
  • Part A hospital coinsurance, plus up to 365 extra hospital days if you run out — 100%
  • Skilled nursing facility coinsurance — 100%
  • Foreign travel emergency care — 80%, up to the plan’s limits

The one thing Plan G doesn’t cover is the Part B deductible itself — that $283 a year is yours. After that, for Medicare-covered care, you’re basically done paying, apart from your monthly premiums. That endless stream of 20% shares from the example above? With Plan G in place, Medicare pays its 80%, Plan G pays the 20%, and the drip stops.

One more thing worth knowing: with Original Medicare plus a supplement, you can see any doctor or hospital in the country that accepts Medicare. There’s no network to worry about, no referrals, and for most care no prior authorization standing between you and your doctor. (One honest exception: Medicare is testing a review program in Arizona for a short list of specific services — but there’s still no insurance plan deciding which doctors you can see.) That matters a lot here in Arizona, where people split time between states or want the freedom to go to the best facility for the problem — including Mayo Clinic, which accepts Original Medicare and supplement plans.

When to put it in place

The best time to buy a supplement is in the six months after you’re 65 and have Part B. In that window, insurance companies can’t turn you down or charge you more because of your health. Miss it, and they can ask health questions — and say no.

If you’re already past that window, don’t assume it’s too late. Sometimes there’s still a way in after the window closes — it depends on your health and your situation. Call me and I’ll tell you straight whether it’s worth pursuing.

We’re in the middle of Medicare’s Annual Enrollment Period right now — October 15 through December 7 — which is when most people are thinking about this stuff. But your Medigap decision doesn’t have to wait for a calendar window, and it shouldn’t. Medicare’s gaps don’t wait for open enrollment, and neither do hospital bills.

What I don’t do — and who I point you to

Two things worth saying plainly. I don’t sell Medicare Advantage plans. Some people solve the 20% problem that way — Advantage plans do cap yearly out-of-pocket costs — and if that’s the direction you want, call me and I’ll point you to the right person for it. And I don’t sell Part D drug plans; for prescription coverage, Medicare.gov is the place to compare your options.

What I do is help you understand the gap, run the numbers for your situation, and put the right supplement in place — then answer my own phone when you have questions later.

If you’re turning 65 soon, or you’ve been on Medicare A and B alone and that 20% has started to worry you, let’s talk it through before something happens. A short conversation now beats watching the 20% shares pile up later.

Questions about your Medicare coverage? Call me at (623) 742-3878 or visit www.azhealth.us. I’m a real person, I answer my own phone, and the help is free.


6 Medicare Advantage Disadvantages Worth Knowing Before 2027

Medicare Advantage plans get marketed hard every fall. Zero-dollar premiums, dental, vision, gym memberships — the commercials make it sound like a no-brainer. And for some people, it works out fine.

But going into 2027, the ground is shifting. CMS finalized its 2027 payment rates for these plans: a 2.48% net increase, which works out to about 5% once expected risk-score trends are included. Insurers say even that isn’t keeping pace with what care actually costs — Humana has already told investors it plans to adjust benefits where necessary next year. When money gets tight, benefits are usually where it shows. (For balance: CMS says about 8 in 10 MA enrollees can keep their current plan at the same or a lower premium in 2027, with average premiums ticking down slightly.)

I don’t sell Medicare Advantage, and I’ve put my reasons in writing. But whether you work with me or not, here are six Medicare Advantage disadvantages worth knowing before the year turns.

1. Prior authorization can delay the care you need

Original Medicare has historically made you ask permission far less often than Advantage plans do. A 2026 report from the HHS Office of Inspector General looked at skilled nursing facility admission requests from June 2024, across 19 parent companies covering about 86% of MA enrollment. Plans denied 12% of those requests — and when patients or providers appealed, the plans overturned 95% of the denials. The OIG’s read: some enrollees were initially denied care that was medically necessary. One detail that sharpens the point: only about 18% of those denials were ever appealed. Appeals take time, and if you’re recovering from surgery or a hospital stay, time matters.

One caveat, especially here in Arizona: starting in 2026, CMS began testing prior authorization inside Original Medicare itself, under a pilot called WISeR. It covers six states including ours, and a defined set of outpatient services — narrower than what Advantage plans do, but the line isn’t as clean as it used to be. A Medigap policy doesn’t change that part.

2. Networks decide where you can go

Original Medicare lets you see just about any doctor or hospital in the country that takes Medicare. (For perspective: KFF found Advantage plans included just under half — 48% — of the physicians available to traditional Medicare beneficiaries.) Medicare Advantage HMOs generally require you to stay in-network except for emergencies; PPOs give you some out-of-network coverage, but you’ll pay more for it.

That’s manageable until your longtime specialist leaves the network — and network limits are among the most common Medicare Advantage disadvantages I hear about — or the hospital you trust isn’t covered anymore. It hits harder outside the cities: in 2026, KFF found beneficiaries in the most rural counties had about 20 plans to choose from on average, versus 42 in urban areas — and KFF’s 2027 data shows options shrinking again, with the average beneficiary seeing 28 drug-included plans, down from 32.

3. The low premium and extra perks can shrink

That $0 premium and the dental, vision, and over-the-counter allowances reset every year. Plans can raise premiums, increase copays, and trim supplemental benefits each January. Going into 2027, with insurers openly planning benefit adjustments, the plan that worked great this year can look very different next January — more expensive, less generous, or both.

Senior couple reviewing Medicare plan paperwork

4. Your drug coverage can change under you

Most Medicare Advantage plans bundle in Part D drug coverage, and formularies, pharmacy networks, and coverage rules can all change annually. A medication can move to a higher cost tier or pick up new restrictions in the new plan year. Checking that your premium didn’t change isn’t enough — run every regular prescription through Medicare’s Plan Finder tool before you renew.

5. Your plan can disappear entirely

Sometimes the change is bigger than a benefit tweak: an insurer can drop a specific plan or leave your county altogether. When a plan’s contract actually ends and you don’t pick another Advantage plan, you’re generally moved to Original Medicare — and that move comes with a 63-day window where you have a federal guaranteed right to buy certain Medigap policies. That protection doesn’t apply if your plan was merely consolidated into another one of the insurer’s plans, so it matters which kind of change you’re dealing with.

Either way, it can be genuinely disruptive if you’re in the middle of cancer treatment, rehab, or another complex course of care. New plan, new doctors, new pharmacies, new copays.

6. Getting back to Original Medicare can be harder than leaving was

This is the one people miss. You can leave Medicare Advantage and return to Original Medicare during an enrollment period — but that doesn’t automatically mean you can buy a Medigap policy to cover Original Medicare’s deductibles and coinsurance. Outside your six-month Medigap open enrollment window or a guaranteed-issue situation, insurers in most states can charge you more or deny you based on your health.

Two exceptions worth knowing. First, the trial right: if you joined Medicare Advantage when you first became eligible and leave within the first year, federal law gives you guaranteed-issue rights to buy a Medigap policy. Second, as noted above, if your Advantage plan’s contract ends or it stops serving your area, you generally get that 63-day guaranteed-issue window. But if you leave voluntarily while your plan keeps operating — and you’re past your trial year — you may not have that protection. (A few states are more protective than the federal baseline, so this is a check-your-state situation.)

What to do about these Medicare Advantage disadvantages

I’m not telling you Medicare Advantage is never the right call. I’m telling you to go in with your eyes open — especially for 2027, with plan data already live and open enrollment underway.

Your Annual Notice of Change should have arrived by September 30. If you haven’t seen yours, call your plan. It spells out exactly what’s changing in January. Then check the things that actually matter to you: your doctors, your hospitals, your prescriptions, your premium, your maximum out-of-pocket, and those supplemental benefits. Don’t assume this year’s coverage carries forward unchanged.

And if you’d rather have coverage built for stability — standardized Medigap benefits that are guaranteed renewable, no networks, no disappearing plans — that’s exactly what I do — I help people compare these Medicare Advantage disadvantages against what a supplement offers. Two honest caveats: the standalone Part D drug plan you’d pair with Medigap does change yearly (options are shrinking for 2027, and some buyers face steep premium jumps), and Medigap premiums themselves can rise over time. But the core medical coverage doesn’t reset every January. I’ve explained my thinking here: why I don’t sell Medicare Advantage.

Medicare open enrollment runs October 15 through December 7. If you want a straight answer about what your options actually look like, call or text me at (623) 742-3878. I’ll run your numbers free.

Medicare Open Enrollment 2027 Arizona: The Notices You Shouldn’t Ignore Before October 15

medicare-open-enrollment-2027-arizonaMedicare Open Enrollment 2027 Arizona officially opens October 15 and runs through December 7 — seven weeks to review your coverage and make changes for next year. But the window itself isn’t the hard part; the hard part is the stack of notices that show up beforehand, which most people skim past without realizing what each one is actually telling them.

Medicare Open Enrollment 2027 Arizona: The Notices Already in Your Mailbox

By late September, you should have received your Annual Notice of Change (ANOC) and Medicare & You handbook. The ANOC is the one worth reading closely — it spells out exactly what’s changing in your Medicare Advantage or Part D plan for 2027: copay changes, dropped providers, and medications that may no longer be covered. If a plan is leaving your county or shutting down entirely, that comes as a separate Plan Non-Renewal or Termination Notice, which can arrive at any time and opens its own special enrollment period outside the normal AEP window.

On October 14, the 2027 cost-of-living adjustment (COLA) is announced, and Medicare’s 2027 Part B premium and Part A/B deductibles follow in late October or early November. Those two numbers are what let you actually estimate next year’s costs instead of guessing. IRMAA determination letters and Social Security COLA notices follow in November and December, showing your actual 2027 premiums and any income-based surcharges.

What to Actually Check Before December 7

With the ANOC in hand, confirm three things: that your current doctors and hospitals are still in network, that your medications are still covered at the tier you expect, and that your plan’s costs still fit your budget once the new premium and deductible numbers are out. It’s also worth pulling your 2026 Medicare Summary Notices or Explanations of Benefits to check for services you didn’t actually receive — errors are more common than people assume, and AEP is a natural time to catch them.

If Something Doesn’t Add Up

If your current plan no longer fits — a doctor dropped from the network, a medication moved to a higher tier, or a cost increase that doesn’t work for your budget — Open Enrollment is your window to switch before December 7, with new coverage taking effect January 1. Setting up a my Social Security or Medicare.gov account can get these notices to you by email sooner, so you’re not relying on paper mail timing.

Not sure what your ANOC actually means for your coverage next year?

📞 Call (623) 742-3878

🌐 www.azhealth.us

Free, no-pressure review before December 7 — I’ll help you read through the notices and compare your options.

*This article is for general educational purposes and is not a comparison of specific plans or an endorsement by Medicare or any government agency. Dates and notice descriptions are from Kiplinger’s 2027 Medicare Open Enrollment guide; confirm your own plan’s specific changes directly through your ANOC or Medicare.gov.*

Switching From Medicare Advantage to Medigap: What Arizona Retirees Should Know Before They Try

Medicare EnrollmentChoosing Medicare Advantage at 65 feels like a low-risk decision, especially with a low or zero monthly premium. The catch tends to show up years later: going from Medicare Advantage to Medigap can be much harder than getting into Medicare Advantage ever was. That’s worth knowing this fall, with Medicare’s Annual Election Period running October 15 through December 7.
Why Medicare Advantage to Medigap Is Harder Than It Looks

Federal law bars Medicare Advantage plans from turning you down or charging you more because of your health — you can enroll during your Initial Enrollment Period, the fall Annual Election Period, or a Special Enrollment Period, sick or not. Medigap plays by a different rulebook. You get one federally protected window, the Medigap Open Enrollment Period, which lasts six months and starts the first month you’re both 65 or older and enrolled in Medicare Part B. During those six months, any insurer selling Medigap in your state has to offer you any plan it sells, at its best available rate, regardless of your health history.

After those six months close, federal protections end and state law takes over. In most states, a Medigap insurer reviewing a later application can ask full health questions, charge a higher rate based on the answers, apply a waiting period of up to six months for a pre-existing condition, or decline the application outright.

Why 72 Is the Wrong Age to Try It

A retiree who picked a zero-premium Medicare Advantage plan at 65 often wants Medigap by 72, right around when prior authorization requirements, narrow provider networks, and out-of-network billing start to matter more. By then, a diagnosis or a longer prescription list picked up along the way can turn a simple application into a difficult one — or an impossible one, in a state without extra protections.

What Can Still Open the Door

A few situations restore your guaranteed-issue right, no matter how long it’s been:

Since Arizona doesn’t have one of these state-level protections, the federal six-month window and the situations above are what determine whether you can switch without medical underwriting here.

What to Decide Before Part B Starts

If you’re approaching 65, you’re deciding whether to use the one federally protected chance to buy Medigap on an insurer’s best terms — that decision is worth more weight than just comparing this year’s premium. If you’re already on Medicare Advantage and past your six-month window, it’s worth confirming whether a guaranteed-issue right currently applies to your situation before assuming a later switch is off the table, or assuming it’s automatically available.

Wondering whether a Medicare Advantage to Medigap switch is realistic for you? Call (623) 742-3878 for a free, no-pressure conversation — as an independent broker who doesn’t sell Medicare Advantage, I can walk through what applies to your specific timeline and situation.

This article is for general educational purposes and is not a comparison of specific plans or an endorsement by Medicare or any government agency. Guaranteed-issue rules can be complex and vary by exact circumstance — confirm your specific situation with Medicare.gov, your State Health Insurance Assistance Program (SHIP), or a licensed agent before making a coverage decision.

Humana Is Dropping Medicare Advantage Plans for 2027 — What to Do If You’re Affected

Humana Medicare Advantage Arizona plan changes 2027 notice

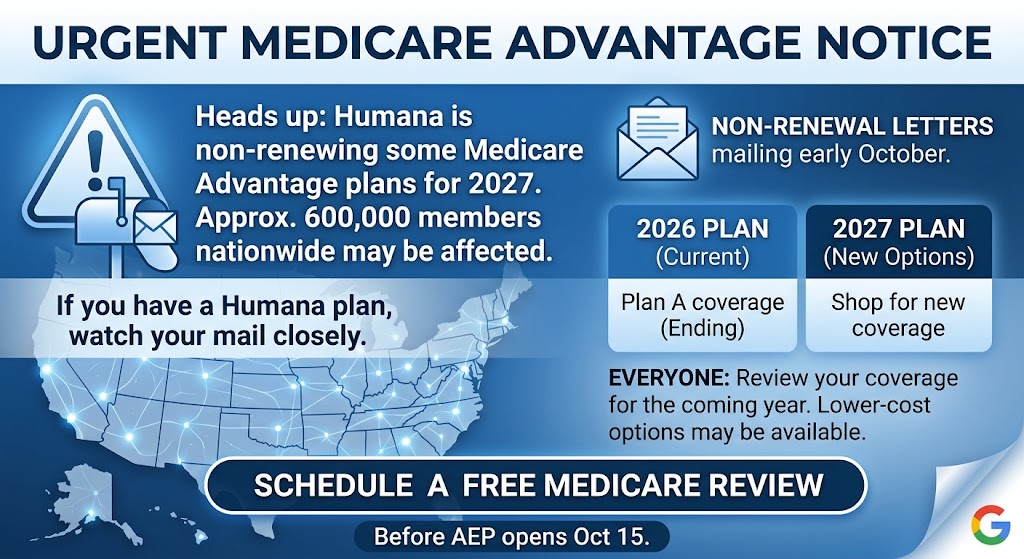
Humana has confirmed it’s exiting a number of Medicare Advantage plans for 2027, affecting roughly 600,000 members nationwide. If you have a Humana Medicare Advantage Arizona plan, this is worth paying attention to — whether or not you’ve received anything in the mail yet.

What’s actually happening

Humana is discontinuing plans it says are the “lower tail of profitability” for 2027 — mostly plans rated 3.5 stars or lower. Non-renewal letters are expected to go out starting in early October, right as Medicare’s Annual Enrollment Period opens on October 15. If your plan is affected, you’ll be notified directly by Humana, but the letter alone won’t tell you what to do next.

Why this matters even if you’re not sure you’re affected

Humana hasn’t published a full list of which specific plans or counties are impacted. The only way to know for certain is to watch your mail closely this fall — and to have a plan for what comes next if a non-renewal letter shows up. Waiting until you’re holding the letter to start comparing options means doing it under time pressure, right in the middle of AEP’s busiest weeks.

Humana Medicare Advantage Arizona: Your Options If Your Plan Is Dropped

If your Humana Medicare Advantage plan is discontinued, you’re not left without coverage — you’ll have a special enrollment window to pick something new. Depending on your situation, that could mean:

As an independent Arizona broker, I’m not tied to steering you back into another Humana Medicare Advantage Arizona product — the goal is finding whatever actually fits your coverage needs now.

What to do this fall

Whether or not you get a letter, it’s worth a quick check-in before AEP opens October 15. If you are notified that your plan is being discontinued, reach out as soon as you get the letter — the sooner we start comparing options, the less rushed the decision.

Received a non-renewal letter, or just want to make sure you’re covered either way? Call (623) 742-3878 for a free, no-pressure review. As an independent Arizona health insurance broker, I can also show you how a Medicare Supplement plan works if you would rather not depend on one plan’s network and market decisions.

This article is for general educational purposes and is not a comparison of specific plans or an endorsement by Medicare, Humana, or any government agency. Please review any notice you receive directly from your carrier for details specific to your plan.

Andy Orlikoff • NPN #7558435 • Licensed in Arizona, North Carolina & South Carolina
Verify this license at nipr.com
Follow us on Facebook
Call Now Get a Quote